
JOURNAL
Intradermal botulinum toxin and antibodies: hypotheses and evidence
Intradermal botulinum toxin and antibodies: hypotheses and evidence. Source observations, research context and limitations.
This article discusses the source author’s earlier literature, cases and experiences. Research populations and limitations matter; individual diagnosis and treatment require clinical assessment.
The source asks whether intradermal toxin might lead to earlier nonresponse than intramuscular treatment. It discusses a hypothesis; direct comparative clinical evidence is needed before asserting a higher or faster rate.
Skin antigen-presenting cells
Skin contains dendritic cells, including Langerhans cells. These participate in antigen presentation and adaptive immunity. Their presence does not alone establish clinical neutralizing-antibody rates after a cosmetic procedure.
The source cites a general immunology statement about dendritic cells linking innate and adaptive immunity. Its exact attribution requires checking.
Antibodies and nonresponse
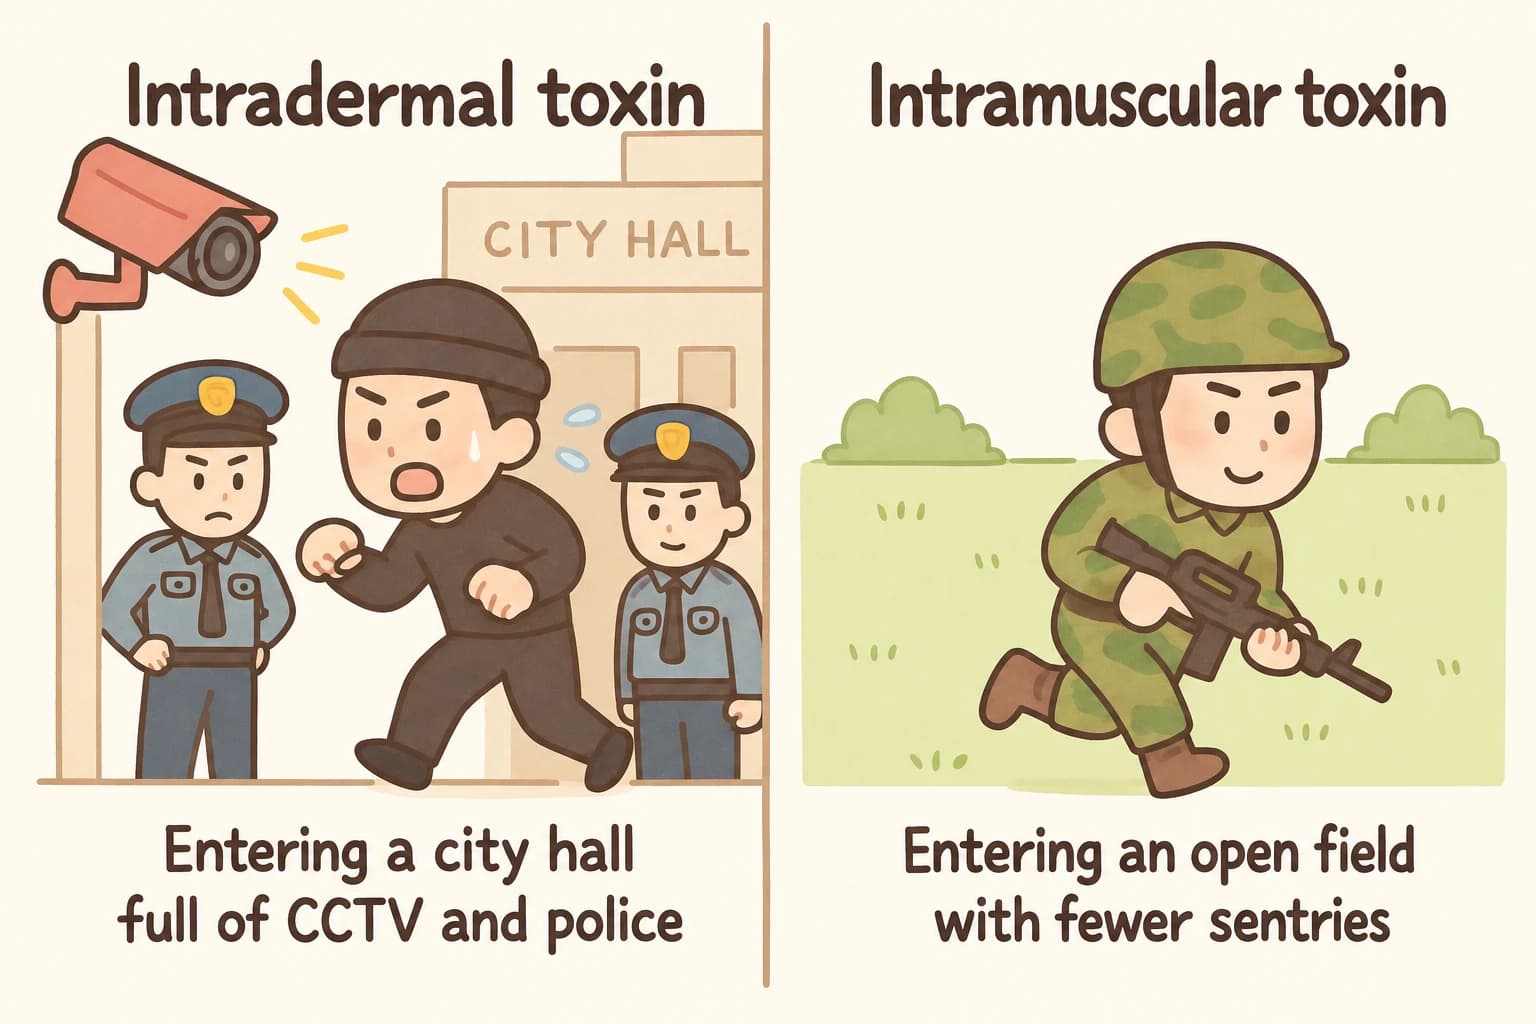
The source describes antigen presentation, T-helper and B-cell responses, and potential neutralizing antibodies. The injected protein does not literally turn into an antibody. A comparison between a lightly guarded field and a crowded police station is only an analogy; it does not prove faster resistance after intradermal injection.
Factors considered in the source
Dose, repeated exposure, intervals, formulation and individual health may matter. Their relative effects require product- and indication-specific evidence; general immune sensitivity or autoimmune disease does not establish a predictable antibody response in an individual.
The source suggests considering long-term treatment planning and total exposure. Combining other treatments does not automatically prevent antibodies or establish a better long-term outcome.
Neutralizing antibodies are one cause of reduced response, but reduced response is not always antibody-mediated. A cellular hypothesis cannot establish that intradermal injections cause more resistance than intramuscular treatment. Review the product, interval, dose and individual situation.
References as listed in the source, with exact bibliographic details requiring reconciliation: Dressler, 2018, on toxin resistance in aesthetic medicine; Nestle et al. on skin immune sentinels; Naumann et al., 2010, on neutralizing antibodies and secondary nonresponse.
This article introduces an evidence question, not a comparison proving one cosmetic product or technique superior.
Source: Original post on Dr. Hyemi Yu’s Naver blog (Korean)
The original publication date and the website revision date are shown separately.